
Powerful Efficacy
Discover the proven efficacy of XCOPRI (cenobamate tablets) CV.
Actor portrayals.


Discover the proven efficacy of XCOPRI (cenobamate tablets) CV.
Powerful reduction across multiple partial-onset seizure subtypes
Results from a study of adult patients with a median of 9 seizures/28 days at baseline1,2
Primary outcome: Patients taking XCOPRI experienced up to 2x greater seizure reduction compared with placebo (55% XCOPRI 400 mg, 55% XCOPRI 200 mg, 36% XCOPRI 100 mg vs 24% placebo)
Secondary outcome: As many as 1 in 5 patients experienced zero seizures with XCOPRI during the maintenance phase (21% XCOPRI 400 mg, 11% XCOPRI 200 mg, 4% XCOPRI 100 mg, 1% placebo)
Additional secondary outcome:
Median percentage reduction in 28-day seizure frequency in
partial-onset seizure subtypes (12-week maintenance phase)1,3
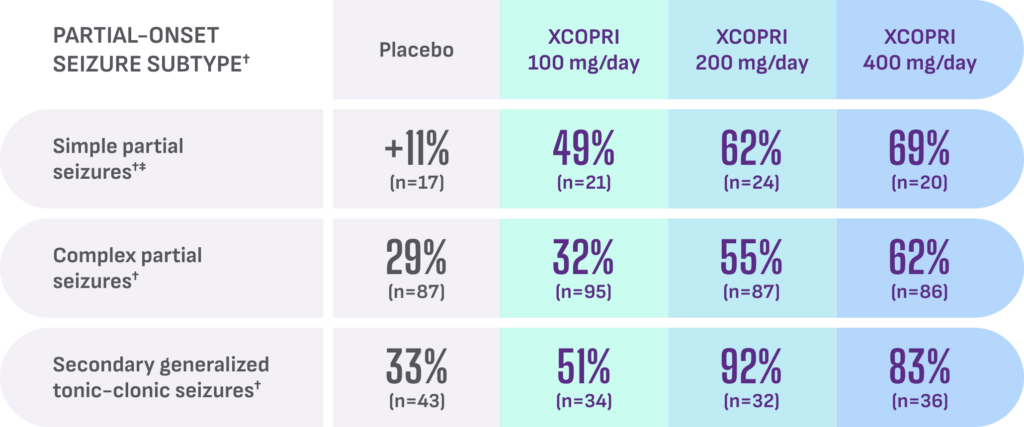
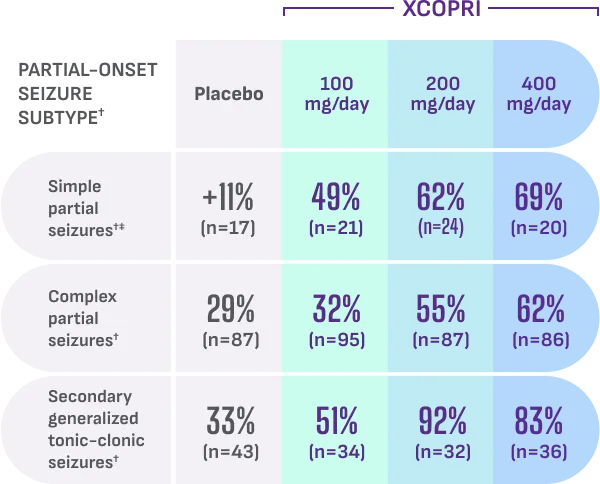
XCOPRI was studied across 2 multicenter, randomized, double-blind, placebo-controlled trials in adult patients with partial-onset seizures with or without secondary generalization.2

1-3
concomitant ASMs were not adequately controlling patients at baseline2§

PLACEBO
Patients in the placebo arm remained on their current ASM1,5

of patients were taking 2 or more concomitant ASMs2

24YEARS
was the approximate duration of epilepsy for patients in both studies2

~9SEIZURES
per 28 days was the median baseline seizure frequency for patients in both studies2
ASMs=anti-seizure medications.
The efficacy of XCOPRI as adjunctive therapy in partial-onset seizures was established in 2 multicenter, randomized, double-blind, placebo-controlled studies in adult patients (Study 1 and Study 2). Patients had partial-onset seizures with or without secondary generalization and were not adequately controlled with 1 to 3 concomitant anti-seizure medications. Study 1 (N=221) compared XCOPRI 200 mg/day with placebo. Study 2 (N=434) compared XCOPRI 100 mg/day, 200 mg/day, and 400 mg/day with placebo. The double-blind treatment period consisted of a titration phase (6 weeks) and a maintenance phase (6 weeks for Study 1 and 12 weeks for Study 2). In both studies, patients were started on a higher daily dosage and/or faster titration than the Prescribing Information recommendation. The primary outcome was median percentage reduction in 28-day seizure frequency during the double-blind treatment period.
In Study 1, patients were started on a daily dosage of 50 mg (a higher starting dosage than currently recommended) and subsequently increased by 50 mg/day every 2 weeks, until the final daily target dosage of 200 mg/day was achieved. In Study 2, patients were started on a daily dosage of 50 mg (a higher starting dosage than currently recommended) and subsequently increased by 50 mg/day every week (a faster titration than currently recommended) until 100 mg/day or 200 mg/day was reached; daily dosage was then increased by 100 mg/day every week in patients randomized to 400 mg/day.
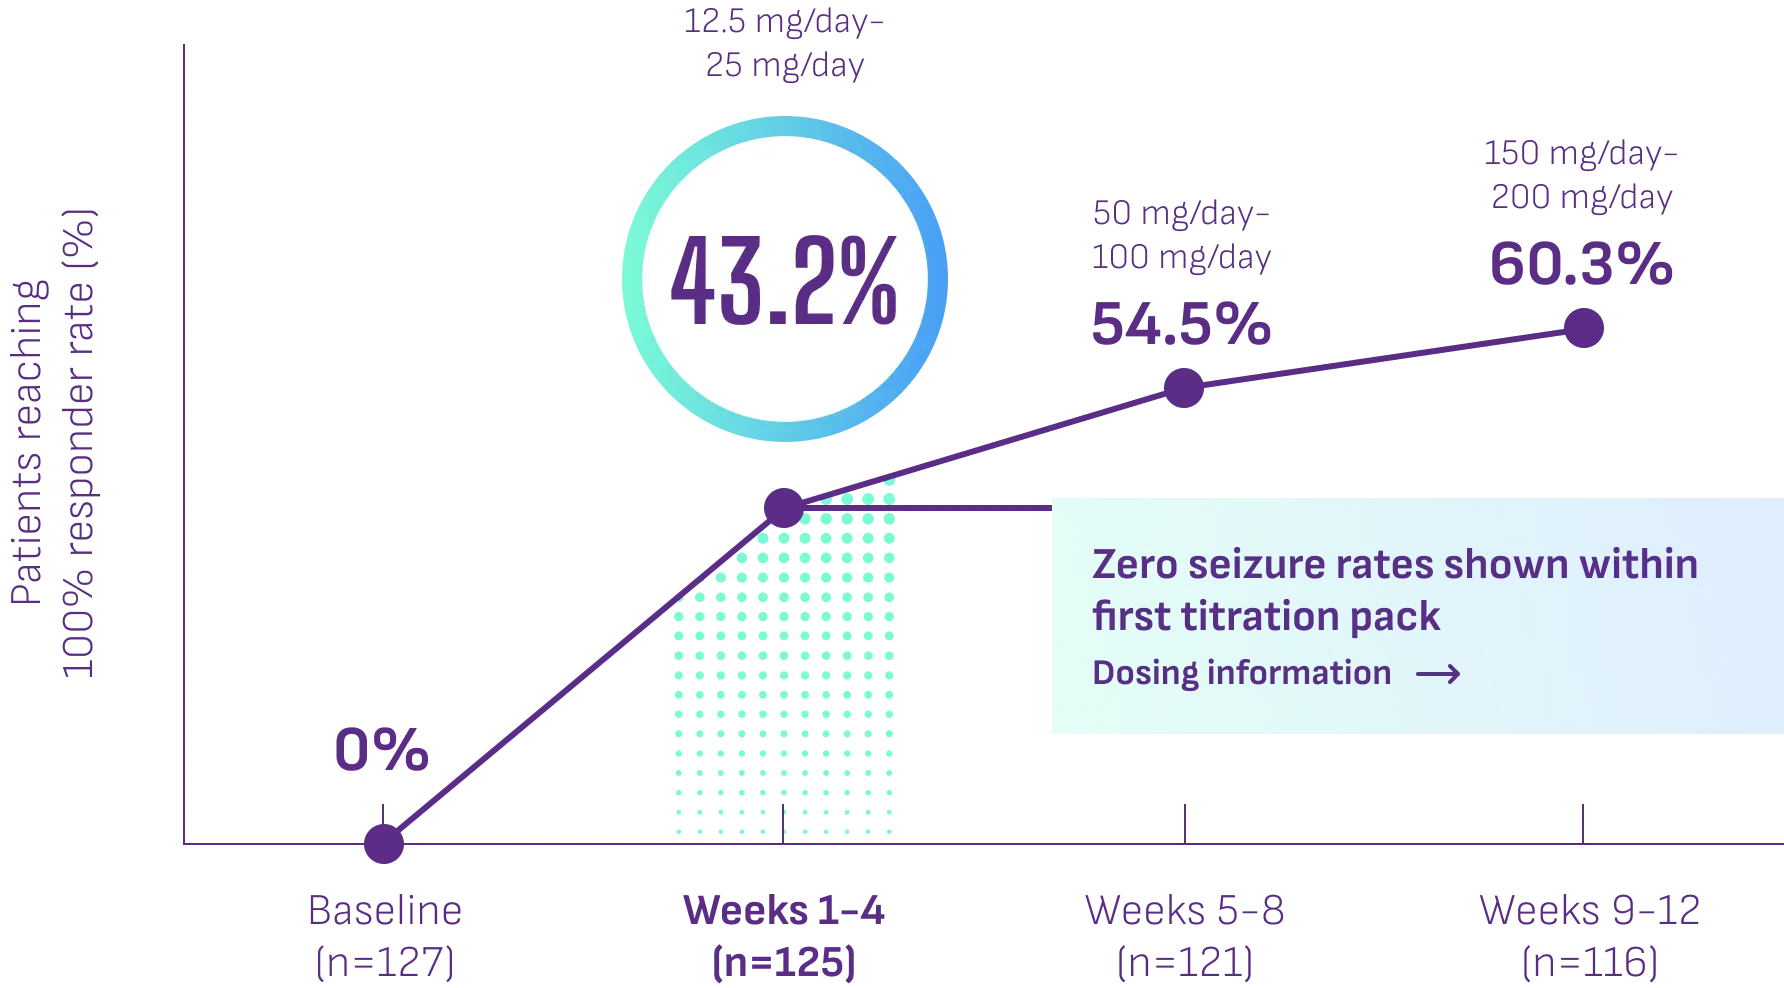
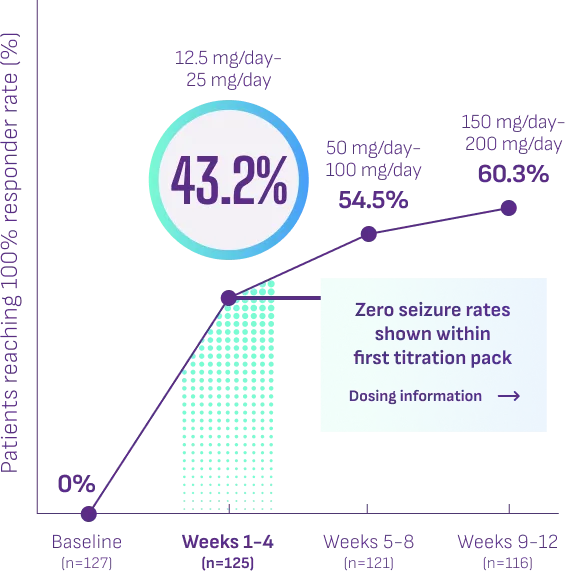
Zero seizure rates achieved within 4 weeks and increased over time6
Results from a post hoc analysis of a phase 3 study: Percentage of patients with 1-2 seizures/28 days
at baseline who achieved zero seizures within the first 4 weeks taking XCOPRI
Limitations: This post hoc analysis of an open-label phase 3 study of XCOPRI did not include a control arm. These data are descriptive and representative of an enriched population with a relatively small number of patients. Appropriate multiplicity adjustments were not applied.
XCOPRI was assessed in a multicenter, open-label safety study in patients 18 to 70 years old with uncontrolled focal seizures despite taking a stable dosage of 1 to 3 anti-seizure medications. The study included a screening period of up to 21 days followed by an open-label treatment period consisting of a 12-week titration phase, followed by an open-label maintenance phase. The maintenance phase continued for the length of the study (total study duration was up to 43 months). Patients initiated XCOPRI treatment using the FDA-approved titration schedule. After reaching 200 mg/day, further increases up to 400 mg/day using biweekly increments of 50 mg/day were allowed during the maintenance phase. Reductions below 200 mg were allowed at investigators’ clinical judgment (minimum allowed dosage was 50 mg/day). XCOPRI monotherapy was not allowed. Patient visits occurred every 2 weeks for 16 weeks and then every 1 to 3 months.
A post hoc analysis in a subset of patients (n=240) evaluated the impact of baseline seizure frequency (<3 seizures/28 days vs ≥3 seizures/28 days) on mean XCOPRI dosage required to achieve 100% seizure reduction, duration of this response, and responder rates. To be eligible for the post hoc analysis, the following criteria must have been met: patients must have had at least 1 focal aware motor, focal impaired awareness, or focal to bilateral tonic-clonic seizure per 13 weeks baseline prior to screening visit; seizure data while on treatment; and consistent documentation of good-quality, raw seizure data for ≥85% of the time spent in the study. Responder rates (≥50%, ≥75%, ≥90%, and 100%) were assessed during the entire treatment period (ie, including during the titration and maintenance phases).
Long-term zero seizure rates seen for 12 months or longer6
Results from a post hoc analysis of a phase 3 study:
Zero seizures achieved with XCOPRI regardless of baseline seizure frequency



Limitations: This post hoc analysis of an open-label phase 3 study of XCOPRI did not include a control arm. These data are descriptive and representative of an enriched population with a relatively small number of patients. Appropriate multiplicity adjustments were not applied.
XCOPRI was assessed in a multicenter, open-label safety study in patients 18 to 70 years old with uncontrolled focal seizures despite taking a stable dosage of 1 to 3 anti-seizure medications. The study included a screening period of up to 21 days followed by an open-label treatment period consisting of a 12-week titration phase, followed by an open-label maintenance phase. The maintenance phase continued for the length of the study (total study duration was up to 43 months). Patients initiated XCOPRI treatment using the FDA-approved titration schedule. After reaching 200 mg/day, further increases up to 400 mg/day using biweekly increments of 50 mg/day were allowed during the maintenance phase. Reductions below 200 mg were allowed at investigators’ clinical judgment (minimum allowed dosage was 50 mg/day). XCOPRI monotherapy was not allowed. Patient visits occurred every 2 weeks for 16 weeks and then every 1 to 3 months.
A post hoc analysis in a subset of patients (n=240) evaluated the impact of baseline seizure frequency (<3 seizures/28 days vs ≥3 seizures/28 days) on mean XCOPRI dosage required to achieve 100% seizure reduction, duration of this response, and responder rates. To be eligible for the post hoc analysis, the following criteria must have been met: patients must have had at least 1 focal aware motor, focal impaired awareness, or focal to bilateral tonic-clonic seizure per 13 weeks baseline prior to screening visit; seizure data while on treatment; and consistent documentation of good-quality, raw seizure data for ≥85% of the time spent in the study. Responder rates (≥50%, ≥75%, ≥90%, and 100%) were assessed during the entire treatment period (ie, including during the titration and maintenance phases).
Reducing concomitant ASM drug load with XCOPRI

Actor portrayals.

Results from a post hoc analysis of a phase 3 study:

of patients on XCOPRI discontinued and/or replaced
1 or more anti-seizure medications (ASMs)
across all drug classes (110/177)7
In this group of patients, there was no increase or addition of concomitant ASMs.7†
The most common concomitant ASMs used at baseline included lacosamide, levetiracetam, lamotrigine, zonisamide, and clobazam.8
GUIDANCE FOR SWITCHING ON XCOPRILimitations: This post hoc analysis of an open-label phase 3 study of XCOPRI did not include a control arm. These data are descriptive and representative of an enriched population with a relatively small number of patients. Appropriate multiplicity adjustments were not applied.
Proven seizure reduction
“XCOPRI is not just for your hard-to-treat patients. XCOPRI may help many of your patients, even those experiencing few seizures or those who were recently diagnosed.”
– David Vossler, MD, FAAN, FAES, FACNS
Watch expert video
10+ years of clinical trial and real-world experience
Well-established safety & tolerability, with over 325,000 patients treated worldwide2*
Review safety profile
Access
XCOPRI is widely accessible with low copays. Discover support available to get started
Learn about access